Sunday, November 28, 2010

How bacteria sort their lipoproteins (Lol!)

Bacterial lipoproteins are proteins with covalently-attached lipid molecules that anchor the protein to the cytoplasmic or outer membrane.  The lipid molecules are attached to the cysteine located at the amino terminus of the lipoprotein.  The lipoprotein's protein component, being hydrophilic (water-loving), sticks out from the membrane. Different bacterial lipoproteins participate in a variety of functions, including transport of molecules, stabilization of the cell wall, signal transduction, motility, and interaction with host molecules.

The Lyme disease spirochete Borrelia burgdorferi is exceptional in that a number of different lipoproteins have been found on its surface.  Most other bacteria lack (or have few) surface-exposed lipoproteins.  To give one example, the figure below shows the arrangement of lipoproteins in the cell envelope of E. coli, home to roughly 90 lipoproteins, none known to be displayed on the surface.  Lipoproteins are depicted as colored ovals with the attached squiggles representing the lipid molecules. To perform their functions properly, some lipoproteins must be anchored to the outer leaflet of the inner membrane (blue ovals) whereas the rest must be anchored to the inner leaflet of the outer membrane (red ovals).  In both cases, the protein component of the lipoprotein protrudes into the periplasm.  The figure also shows the other major category of membrane proteins, the integral membrane proteins, which are embedded in the membrane.  There are also proteins that reside in the periplasm, which are not depicted in the figure.


In this post I will describe how lipoproteins are brought to their correct location in the bacterial envelope.  I will first describe how lipoproteins are sorted in E. coli since that's where most of the earlier work was conducted. Since many other diderms (bacteria having two membranes) have homologs of the proteins used by E. coli to export and sort lipoproteins, E. coli is a good model for studying localization of lipoproteins.  Monoderm bacteria also have lipoproteins, but since they have only one membrane, they don't need to worry about sorting lipoproteins.  (I will save the explanation of how lipoproteins get to the bacterial surface for a future post.)

Most proteins to be exported out of the cytoplasm are marked with an amino-terminal signal peptide ≈20 amino acids in length.  The sequences of the signal peptides (plus five additional amino acid residues) from two E. coli lipoproteins are shown below.  A cytoplasmic membrane protein complex called the Sec translocon transfers proteins harboring the signal peptide to the periplasm, where the signal peptide is lopped off by one of two signal peptidases.  Signal peptidase I cleaves off the signal peptide from nonlipoproteins (such as periplasmic or transmembrane outer membrane proteins), and signal peptidase II slices off the signal peptide from lipoproteins.

All lipoproteins harbor a short sequence called a "lipobox" at the end of the signal peptide (underlined in sequences below).  The lipobox consensus sequence  is -(leu, ala, val)-4-leu-3-(ala, ser)-2-(gly, ala)-1↓cys+1, with the arrow specifying the cleavage site for signal peptidase II and the subscripts denoting positions relative to the cleavage site.

E. coli Braun's lipoprotein (OM) MKATKLVLGAVILGSTLLAGCSSNA...
E. coli lpp-28 (IM)           MKLTTHHLRTGAALLLAGILLAGCDQSS...

(IM, inner membrane; OM, outer membrane)

The lipobox is recognized by the inner membrane enzyme phosphatidylglycerol:prolipoprotein diacylglyceryl transferase (Lgt).  Before the signal peptide is removed, Lgt attaches diacylglycerol to the sulfhydryl (-SH) of the lipobox cysteine.  After the signal peptide is cleaved off by signal peptidase II, another inner membrane enzyme, apolipoprotein N-acyltransferase (Lnt), attaches a fatty acid molecule to the newly exposed amino (-NH3) group of the cysteine.  Only exported proteins with lipoboxes become lipidated.  The lipoprotein remains associated with the inner membrane throughout these processing steps.

The machinery responsible for sorting lipoproteins to the outer membrane is the LolCDE protein complex, a type of ABC transporter that sits in the inner membrane.  Lol stands for lipoprotein outer membrane localization.  LolCDE recognizes the lipidated cysteine at the amino terminus of lipoproteins.  LolCDE loads lipoproteins onto the periplasmic protein LolA, which ferries lipoproteins to the LolB receptor, a lipoprotein that protrudes from the periplasmic face of the outer membrane.  After capturing the lipoprotein from LolA, LolB anchors the lipoprotein into the periplasmic layer of the outer membrane.

from figure 3 of Tokuda and Matsuyama (2004)

How does LolCDE know which lipoproteins are supposed to be delivered to the outer membrane and which need to stranded in the inner membrane?  For E. coli and other members of the Enterobacteriaceae family of bacteria, the answer is fairly simple.  Lipoproteins with aspartate at the +2 position (which follows the lipidated cysteine) remain in the inner membrane.

How does the +2 aspartate prevent transfer of lipoproteins to the outer membrane?  It turns out that LolCDE doesn't directly sense the amino acid at the +2 position.  Instead, the abundant membrane phospholipid phosphatidylethanolamine (PE) is thought to interfere with LolCDE recognition of the lipidated cysteine when asparatate is at the +2 position.  When the side chain carboxyl group (-COO-) of the +2 aspartate interacts electrostatically with the positively-charged head group of PE, the fatty acids of PE become perfectly positioned to form hydrogen bonds with the lipid molecules attached to the cysteine (see figure below).  LolCDE is unable to recognize the amino-terminal cysteine associated with five fatty acid groups (three covalently bound to the cysteine and two from PE).  Thus asparatate, when it follows the cysteine, acts indirectly as a Lol avoidance signal.  The amino acid at the +3 position can also influence the Lol avoidance signal.  For example, negatively-charged amino acids (aspartate and glutamate) at the +3 position strengthen the +2 aspartate Lol avoidance signal by stabilizing the complex between phosphotidylethanolamine and the +2 aspartate (see figure below).

Modified from figure 6 of Tokuda and Matsuyama (2004)

Additional studies with engineered lipoproteins have shown that phenylalanine, tryptophan, tyrosine, lysine, and proline, although rarely found in lipoproteins at the +2 position, can also serve as inner membrane retention signals when asparagine is at the +3 position.  Since none of these are negatively-charged amino acids, the mechanism for avoiding LolCDE must differ from those lipoproteins having aspartate at the +2 position.

The nature of the sorting signal differs for bacteria that are not members of Enterobacteriaceae.  For example, the three amino acids at positions +2 through +4 dictate whether lipoproteins will remain in the inner membrane of Pseudomonas aeruginosa.  For the spirochete B. burgdorferi, a clear rule has yet to emerge from the few studies that have been done.  What can be said is that negatively-charged amino acids (aspartate and glutamate) placed within the first several amino acids following the lipidated cysteine sometimes allows the lipoprotein to remain in the membrane.  Whether the negatively-charged amino acid functions as an inner membrane retention signal depends on which amino acids are surrounding it.  It is not yet possible to simply look at the amino-terminal sequence of B. burgdorferi lipoproteins and confidently predict in which membrane they will be found.

ResearchBlogging.orgAlthough the "+2/+3/+4 rule" is useful for predicting whether a newly discovered lipoprotein will be found in the inner or outer membrane, it may not give the complete picture of all of a lipoprotein's features that govern its localization.  The rules for sorting lipoproteins were worked out primarily by examining the localization of engineered fusion proteins consisting of the amino termini of lipoproteins (signal peptide with lipobox plus the first several amino acids following the lipobox cysteine) fused to unrelated reporter proteins such as red fluorescent protein (RFP) from corals.  For example, placing asp at the +2 position of such a fusion protein would cause RFP to be retained in the inner membrane.  Changing the +2 amino acid to serine would cause RFP to be transported to the outer membrane.  However, localization of a full-length lipoprotein may not be altered by simply changing its +2 amino acid from aspartate to another amino acid or vice versa.  This indicates that the rest of the lipoprotein, the part that's removed when reporters are used, also influences the localization of lipoproteins.


References

TOKUDA, H. (2009). Biogenesis of outer membranes in Gram-negative bacteria. Bioscience, Biotechnology, and Biochemistry, 73 (3), 465-473 DOI: 10.1271/bbb.80778

TOKUDA, H. (2004). Sorting of lipoproteins to the outer membrane in E. coli. Biochimica et Biophysica Acta (BBA) - Molecular Cell Research, 1693 (1), 5-13 DOI: 10.1016/j.bbamcr.2004.02.005

Schulze, R., & Zückert, W. (2006). Borrelia burgdorferi lipoproteins are secreted to the outer surface by default. Molecular Microbiology, 59 (5), 1473-1484 DOI: 10.1111/j.1365-2958.2006.05039.x

Sunday, August 1, 2010

The major outer membrane protein of Leptospira interrogans: Not essential for infection?

Because leptospirosis is a potentially fatal disease, it would be worthwhile to figure out which of the many genes on the two chromosomes of Leptospira express products that are essential for infection.

The lipoprotein LipL32 is the most abundant outer membrane protein found in the outer membrane of pathogenic species of Leptosipra. It's been assumed that LipL32 plays an important role in infections for the following reasons:
  • LipL32 is found only in pathogenic species of Leptospira. Nonpathogenic species such as L. biflexa lack the gene encoding LipL32.
  • LipL32 peaks out on the surface of Leptospira, where it is available to interact directly with host molecules.
  • LipL32 binds (at least weakly) to several components of the extracellular matrix.
  • Leptospirosis patients generate a strong antibody response against LipL32.
  • The protein sequence of LipL32 among different species of Leptospira is almost identical.
  • A lot of metabolic energy must be expended to make the large amounts of LipL32 found in the spirochete.
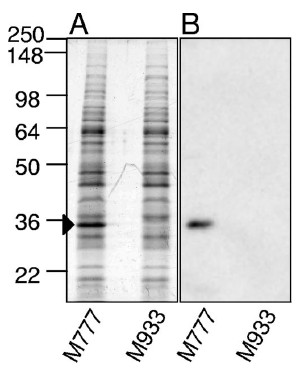
Although a lipL32 knockout mutant would help scientists figure out whether LipL32 plays an essential role in pathogenesis, targeted gene disruptions are extremely difficult with pathogenic Leptospira.  Fortunately, Ben Adler's group at Monash University obtained an insertion mutation in the lipL32 gene of L. interrogans by transposon mutagenesis.  This gave the Australians and their collaborators an opportunity to test the role of LipL32 in causing lethal infections in the hamster model of leptospirosis.  They first confirmed that the lipL32 mutant failed to express LipL32 by Western blotting the mutant with LipL32 antiserum.  I am showing the Coomassie-blue stained protein gel of the whole-cell lysate below so that you can appreciate the abundance of LipL32.  It is the most intensely stained band in the control L. interrogans strain, which has its lipL32 gene intact.

Whole-cell lysates of the L. interrogans lipL32 mutant (M933) and a control strain with the transposon in an intergenic region (M777) were run into SDS-acylamide gels and stained (panel A) or analyzed by Western blotting with LipL32 antiserum (panel B).  The M777 strain was demonstrated in an earlier study to be lethal for hamsters.  (Figure 1 from Murray et al., 2009.)

The survival curves show that the L. interrogans lipL32 mutant was just as lethal to hamsters as the parent L. interrogans with its lipL32 gene intact, irrespective of the infection route.  Hence, lipL32 is not necessary for lethal infections of hamsters, at least under the conditions used in this study.

Panel A: Groups of 8 hamsters were inoculated with 1,000 leptospires into the abdominal cavity.  Panel B:  Groups of 10 hamsters were inoculated with 106 leptospires dropped into the eye.  The slight difference in the survival curves was not statistically significant.  (Figure 5 from Murray et al., 2009)


Rats are the natural reservoir hosts of L. interrogans.  They can carry the spirochete for years in their kidney tubules without showing any signs of illness.  LipL32 could have a role in chronic infections.  The investigators therefore tested the ability of the lipL32 mutant to establish a chronic infection in laboratory rats.  They found that the lipL32 mutant (M933) was able to colonize the rat kidneys as well as the control M777 strain.  Kidneys from all 8 rats inoculated with the lipL32 mutant were culture positive.

At first glance it's surprising that lipL32 was not required for acute or chronic infection.  The authors pointed out that the function of LipL32 could be copied by other proteins found on the surface of Leptospira.  However, the study could have been strengthened by making two changes.  First, since the authors were trying to determine whether lipL32 was necessary for chronic infection, the rats should have been allowed to live for at least a few months before their kidneys were cultured.  Instead, the infection was allowed to proceed for only 15 days before the rats were sacrificed.  Second, they should have measured the bacterial load in the rat kidneys, either by plating serial dilutions of the kidney homogenates for colonies (although I don't know if this is feasible for Leptospira) or by quantitative PCR.  Clearly, more work needs to be done before anyone can conclude that LipL32 is not essential for chronic infection.


Featured paper

Murray G.L., Srikram, A., Hoke, D.E., Wunder Jr., E.A., Henry, R., Lo, M., Zhang, K., Sermswan, R.W., Ko, A.I., and Adler, B. (March 2009).  Major surface protein LipL32 is not required for either acute or chronic infection with Leptospira interrogansInfection and Immunity 77(3):952-958.  DOI: 10.1128/IAI.01370-08


Related posts

Saturday, July 24, 2010

Antigen presentation in the bloodstream: How invariant NKT cells are activated by Lyme disease spirochetes

The spirochete Borrelia burgdorferi is the tick-borne agent of Lyme disease, which affects the joints, nervous system, and heart.  After being deposited into the skin by an infected tick, the spirochete must enter the bloodstream so that it can circulate in the blood to gain access to its target organs.

The host doesn't sit idly as B. burgdorferi establishes an infection.  Invariant natural killer (iNKT) cells are one of the tools deployed by the immune system in its battle against the Lyme spirochetes.  Scientists know this because B. burgdorferi-infected mice lacking iNKT cells ended up with more spirochetes in their tissues and greater joint swelling than mice with a complete immune system.2

iNKT cells are an odd type of T cell.  Like other T cells, iNKT cells have a T cell receptor (TCR), yet they also express protein markers used to identify natural killer (NK) cells.  What makes the iNKT cell invariant is its TCR α chain, which comes only in the version dubbed Vα14 in mice and Vα24 in humans.  Even the β chain of the TCR of iNKT cells is restricted to three types in mice and just one in humans.  The lack of variation is unusual because the α and β TCR chains of conventional αβ T cells come in many forms in each individual, resulting in millions of varieties of TCRs.  This enables conventional αβ T cells to recognize a wide range of microbial peptide antigens when displayed by an MHC molecule on the surface of an antigen-presenting cell (see figure below).  In contrast, the TCRs of iNKT cells recognize a limited set of glycolipids displayed by the antigen-presenting cell's CD1d molecule, which structurally resembles MHC.  So far these glycolipids have been found only in Sphingomonas and B. burgdorferi.

Antigen recognition by T cells.  The "X" represents variable T cell receptor chains.
Figure 1 from ref. 3.
The structures of the B. burgdorferi glycolipids recognized by iNKT cells are shown below.  BbGL-IIc is recognized by mouse iNKT cells, and BbGL-IIf reacts with human iNKT cells.4
Structures of B. burgdorferi glycolipid antigens recognized by iNKT cells.  Figure 3d from ref. 3.

iNKT cells are activated when their TCR binds to BbGL-II complexed with CD1d.4  The activated iNKT cells secrete cytokines that elicit the appropriate immune response against the spirochetes.  How these cytokines promote killing of B. burgdorferi remains unknown.

To view the process of iNKT cell activation, scientists have recently obtained video footage of the early stages of the immune response to Borrelia burgdorferi circulating in the bloodstream of mice.1  The study by Lee et al., which appeared in the April issue of Nature Immunology, complements two earlier studies that revealed how the Lyme disease spirochete escapes from the bloodstream of mice to invade the surrounding tissues.5,6

The investigators employed fluorescence video microscopy to watch the immune cells in action following injection of an engineered B. burgdorferi strain expressing green fluorescent protein (GFP) into the bloodstream.  Although the spleen is better known for filtering bloodstream pathogens, the liver was selected for observation because iNKT cells make up 30% of the T cells in the liver.  In contrast, iNKT cells represent only 2.5% of T cells in the spleen.  Moreover, mice missing their spleen were able to limit B. burgdorferi infection as well as mice having a spleen, suggesting that the spleen is not critical in fighting bloodstream B. burgdorferi.

iNKT cells reside in the liver's sinusoids, which are the specialized capillaries that carry blood through the liver.  Similar to what other investigators have observed, the authors saw iNKT cells creeping along the inner surface of the liver sinusoids in healthy mice (see video below).

iNKT cells crawling within the liver sinusoids of a mouse genetically altered to express green fluorescent protein (GFP) in iNKT cells.  The iNKT cells glow bright green.  The elapsed time is shown at the top right.  Video 2 from ref. 1.

The investigators wanted to figure out which of the antigen-presenting cells found in the liver presented borrelial glycolipid to iNKT cells.  The answer?  After the spirochetes were injected into the bloodstream, they were quickly captured by Kupffer cells, the specialized blood-filtering macrophages that also reside in the liver sinusoids (see figure below).  Unlike iNKT cells, Kupffer cell remained stationary.

Capture of fluorescent B. burgdorferi (thin green bodies) by Kupffer cells (arrowhead).  Kupffer cells are stained red.  B. burgdorferi that avoided capture can be seen bound to the endothelium, trying to escape from the bloodstream into the liver tissue (arrow).  Figure 2e from ref. 1.

During the next several hours, the captured spirochetes were engulfed and broken up by the Kupffer cells so that BbGL-II could be loaded onto CD1d and displayed on the cell surface.  At 8 hours post injection, iNKT cells started to cluster and form stable contacts with Kupffer cells.  The iNKT cells were attracted to Kupffer cells churning out the chemokine CXCL9, a potent iNKT cell attractant.  The evidence for this was that injection of antibodies against the CXCL9 receptor, located on the iNKT cell surface, blocked clustering of iNKT cells.  Interaction of the Kupffer and iNKT cells was accompanied by increased blood and liver levels of the cytokine IFN-γ (interferon-gamma), a sign that the iNKT cells were being activated.

Left panel:  Liver 24 hours after injection of a GFP+ strain of B. burgdorferi into the bloodstream of a mouse.  Arrows indicate spirochetes (thin green bodies) that were not captured.  Kupffer cells are stained a red. The iNKT cells are the large bright green bodies.  The bright iNKT clusters overwhelm the faint red Kupffer cells, which are difficult to see.  Right panel:  To obtain a more convincing image showing contact between Kupffer cells and iNKT cells, a 3D reconstruction of the optical sections through the liver was performed.  Rotation of the image reveals interactions between Kupffer and iNKT cells.

Not all spirochetes were captured.  The investigators saw B. burgdorferi escaping from the sinusoids into the surrounding liver tissue even as other spirochetes were trapped by nearby Kupffer cells (see figures above).  Spirochetes circulating throughout the host probably escaped into other organs in the same manner.  Indeed, large amounts of  B. burgdorferi DNA were detected by PCR in several organs, including the liver, three days after the spirochetes were injected.  Although one doesn't usually think about the effects of Lyme disease on the liver, the authors pointed out that a mild hepatitis is common in Lyme disease patients.  In one prospective study, 40% of Lyme disease patients had at least one liver test abnormality.7

ResearchBlogging.orgBy now you may be wondering why the liver would devote such a high percentage of its T cells towards recognizing glycolipids that aren't found on most bacteria.  One answer is that microbes lacking the proper glycolipids may activate iNKT cells indirectly.3  For example, Salmonella typhimurium uses its LPS to coax antigen-presenting cells into making an endogenous glycolipid that gets presented to the iNKT cell by CD1d.8  It is also possible that glycolipids that are recognized by iNKT cells are present in other bacteria but are yet to be discovered.


Featured paper

1. Lee, W.Y., Moriarty, T.J., Wong, C.H.Y., Zhou, H., Strieter, R.M., van Rooijen, N., Chaconas, G., & Kubes, P. (2010). An intravascular immune response to Borrelia burgdorferi involves Kupffer cells and iNKT cells Nature Immunology, 11 (4), 295-302 DOI: 10.1038/ni.1855

Other references

2.  Tupin, E., Benhnia, M.R., Kinjo, Y., Patsey, R., Lena, C.J., Haller, M.C., Caimano, M.J., Imamura, M., Wong, C., Crotty, S., Radolf, J.D., Sellati, T.J., and Kronenberg, M. (2008).  NKT cells prevent chronic joint inflammation after infection with Borrelia burgdorferiProc. Natl. Acad. Sci. USA 105(50):19863-19868.  DOI: 10.1073/pnas.0810519105

3.  Tupin, E., Kinjo, Y., and Kronenberg, M. (2007).  The unique role of natural killer T cells in the response to microorganisms.  Nature Reviews Microbiology 5(6):405-417.  DOI: 10.1038/nrmicro1657

4.  Kinjo, J., Tupin, E., Wu, D., Fujio, M., Garcia-Navarro, R., Benhnia, M. R., Zajonc, D.M., Ben-Menachem, G., Ainge, G.D., Painter, G.F., Khurana, A., Hoebe, K., Behar, S.M., Beutler, B., Wilson, I.A., Tsuji, M., Sellati, T.J., Wong, C., and Kronenberg, M. (2006).  Nature Immunology 7(9):978-986.  DOI: 10.1038/ni1380

5.  Moriarty, T.J., Norman, M.U., Colarusso, P., Bankhead, T., Kubes, P., and Chaconas, G. (June 20, 2008).  Real-time high resolution 3D imaging of the Lyme disease spirochete adhering to and escaping from the vasculature of a living host.  PLoS Pathogens 4(6):e1000090.  DOI: 10.1371/journal.ppat.1000090

6. Norman, M.U., Moriarty, T.J., Dresser, A.R., Millen, B., Kubes, P., and Chaconas, G. (October 3, 2008). Molecular mechanisms involved in vascular interactions of the Lyme disease pathogen in a living host.  PLoS Pathogens 4(10):e1000169.  DOI: 10.1371/journal.ppat.1000169

7.  Horowitz, H.W.,  Dworkin, B., Forseter, G., Nadelman, R.B., Connolly, C., Luciano, B.B., Nowakowski, J., O'Brien, T.A., Calmann, M., Wormser, G.P. (June 1996).  Liver function in early Lyme disease.  Hepatology 23(6):1412-1417.  DOI: 10.1002/hep.510230617

8.  Mattner J., DeBord, K.L., Ismail, N., Goff, R.D., Cantu III, C., Zhou, D., Saint Mezard, P., Wang, V., Gao, Y., Yin, N, Hoebe, K., Schneewind, O., Walker, D., Beutler, B., Teyton, L, Savage, P.B., and Bendelac, A. (March 24, 2005).  Exogenous and endogenous glycolipid antigens activate NKT cells during microbial infections.  Nature 434(7032):525-529.  DOI: 10.1038/nature03408

Related posts

Tuesday, June 22, 2010

Congenital syphilis, upward trend (again) in the United States

Syphilis can be deadly if passed from an infected mother to her unborn child. The most recent CDC data show that 6.5% of U.S. infants with congenital syphilis (CS) in 2008 were stillborn or died within 30 days of birth.1

Newborns with CS who are destined to live begin to show signs of disease within the first few weeks of life.  The main features of CS in early infancy include fever, skin lesions, enlarged liver and spleen, and a chronic runny nose ("snuffles"), which may be tinged with blood.  Bone lesions may lead to Parrot's pseudoparalysis, a condition so painful that the infant will refuse to move the affected extremities.  Ongoing damage to bony tissue may later lead to childhood deformities including saddle nose, sabre shins, and Hutchinson incisors (notched central incisors).  Other late signs of CS include inflammation of the cornea and sudden hearing loss.

The lesions and deformities associated with congenital syphilis are sparked by Treponema pallidum, a spirochete that can cross the placenta from the mother's bloodstream.  The probability of transmission to the fetus depends on how long the mother has been infected with T. pallidum.  The risk of transmission is lower in mothers at later stages of syphilis.  After crossing the placenta, the spirochete invades the fetal organs.  The continuing immune response to persistent T. pallidum infection causes the damage seen in CS.  Early treatment of the mother with penicillin, at least 30 days before delivery, is essential to stop the disease.

The rate of congenital syphilis in the United States has started to creep back up after plummeting over two decades.1  The incidence of congenital syphilis has gone up from 8.2 cases per 100,000 live births in 2005 to 10.1 in 2008 with most of the increase having occurred in the South.  CS rates in infants born to black mothers have gone up from 26.6 in 2005 to 34.6 per 100,000 live births in 2008 and now account for half of all CS cases.  Since CS is transmitted from mothers with syphilis, CS rates have historically tracked the combined primary and secondary syphilis rate seen in women, which has also started to climb (see figure below).  What factors account for the increased incidence of syphilis?  In one Alabama county, increased syphilis rates in black women were linked to crack cocaine use and the exchange of sex for money or drugs.2  Although more studies are needed to determine whether the same factors are linked to syphilis throughout the South, it should be pointed out that the same factors were associated with the previous syphilis epidemic that peaked in the early 1990s, when there were several thousand yearly cases of CS as opposed to the several hundred seen today.3

Figure from CDC1

Now that the upward trend in the CS rate has been recognized, public health authorities in partnership with community-based groups must allocate some of their scarce resources to reverse the trend.  With prenatal care and prompt treatment, congenital syphilis can be prevented.

1. Centers for Disease Control and Prevention (CDC) (April 16, 2010). Congenital syphilis - United States, 2003-2008. MMWR Morbidity and Mortality Weekly Report 59(14):413-417.  link

2. Centers for Disease Control and Prevention (CDC) (May 8, 2009).  Primary and secondary syphilis - Jefferson County, Alabama, 2002-2007.  MMWR Morbidity and Mortality Weekly Report 58(17):463-467.  link

3. Nakashima, A.K., Rolfs, R.T., Flock, M.L., Kilmarx, P., and Greenspan, J.R. (Jan-Feb 1996). Epidemiology of syphilis in the United States, 1941-1993.  Sexually Transmitted Diseases 23(1):16-23.  PMID: 8801638

Friday, April 30, 2010

Healthy human carriers of the spirochete Leptospira in the Peruvian Amazon

The spirochete Leptospira is the agent of leptospirosis, a zoonosis that primarily burdens tropical regions of the world.  Moist conditions promote the survival of Leptospira in soil and fresh water. Although Leptospira could survive out in wet environments if they had to, they thrive in the kidneys of rats and other maintenance hosts, where they form dense masses lining the inner surface of the kidney tubules.  The spirochetes spill into the urine that forms in the tubules, which drain into the bladder.  Animals colonized by their "preferred" serovar (immune type) shed Leptospira throughout their lives without ever showing signs of illness.  The tainted urine ends up contaminating soil and water with infectious Leptospira.

Humans aren't regarded as long-term carriers of Leptospira.  Rather, they are deemed "accidental" (incidental) hosts who may suffer serious complications of acute disease, including kidney failure and lung hemorrhage.  Humans get infected when they come into contact with contaminated water or soil or following direct exposure to infectious animal urine or tissue.  Leptospira enters through cuts in the skin or mucous membranes.  From there the motile spirochete spreads via the bloodstream and invades internal organs, including the kidneys, where they remain for the duration of the disease.  Patients typically stop releasing Leptospira into their urine after they recover from the illness, presumably because the spirochetes have been eliminated from their kidneys.  However, there have been a few reports of Leptospira excreted in urine months or even years following recovery from leptospirosis.  The truth is that no one has ever done a systematic study to determine how common the chronic carrier state is in humans.

A team of investigators from the United States and Peru set out to find long-term carriers of Leptospira.  Their study is described in the February issue of PLoS Neglected Tropical Diseases.  The authors examined the inhabitants of a rural Amazon village of Padrecocha near the city of Iquitos, Peru, where leptospirosis is endemic. The tropical climate is ideal for the survival of Leptospira in the moist environment favored by the spirochete.  Indeed, in an earlier study the authors detected infectious strains of Leptospira in the streams and wells serving the village.  Cattle, pigs, dogs, and rats, all potential carriers, freely roam the area.

Ganoza and colleagues wanted to determine what percentage of the villagers were chronic carriers of Leptospira.  They first identified villagers who were not recently infected with Leptospira.  Out of the 314 healthy villagers enrolled in the study, 102 (32.5%) had no clinical or serological evidence of recent infection; they did not recall experiencing a fever during the previous year (fever is a typical symptom of leptospirosis), and they tested negative for newly-acquired Leptospira infection by IgM ELISA.

The investigators next identified those whose kidney were colonized by Leptospira among the 102 who were not newly infected.  Since Leptospira living in the kidney tubules are shed into urine, they screened urine samples by nested PCR using primers targeting the 16S rRNA gene of Leptospira.  To exclude false-positive signals, the investigators screened the PCR-generated DNA (amplicon) by dot blot analysis with a Leptospira 16S rRNA probe.  Many false positive signals occurred because their Leptospira PCR primers also hybridized to the 16S rRNA gene from Atopobium vaginae, a bacterium recently found to be associated with vaginosis

When urine from the 102 "long-term" healthy individuals was screened, Leptospira DNA was found in 6 (5.9%).  Sequencing of the 16S rRNA gene revealed that the carriers were colonized with L. interrogans, L. fainei, and L. licerasiae.  So it turns out that the asymptomatic carrier state is not as rare as initially believed.  More than 1 in 20 individuals who had been healthy for at least a year were colonized with Leptospira in their kidneys.

The investigators found seven additional individuals colonized with Leptospira by screening urine from the other 212 individuals in the study.  Overall the percentage of shedders of Leptospira among all healthy individuals, irrespective of when they were infected, was 4.1% (13/314).  The concentration of Leptospira in the urine of shedders, as measured by quantitative PCR, was low, in the 102-104/ml range.  In contrast, rats may shed up to 108 spirochetes/ml!

The study unearthed another surprise.  All 13 individuals who were shedding Leptospira at the time of the study (including the 6 chronic carriers) were women.  The proportion of women with Leptospira DNA in their urine (13/13, 100%) was significantly higher than the proportion of women in the group lacking detectable DNA in their urine (199/301, 66%, p = 0.011).  This result raises the possibility that women are more likely to become persistent carriers than men.  However, the authors pointed out that men were underrepresented in the study sample.  Less than one third of the villagers enrolled in the study were men.  Most of the other men were away at work when the authors were recruiting people for the study.  Agricultural occupations, which bring workers into contact with environmental sources of Leptospira, are well-known risk factors for infection by the spirochete in endemic areas.  Hence, male shedders of Leptospira may have been inadvertently excluded from the study.

Another surprising result was that sera from all six chronic carriers failed to agglutinate Leptospira by MAT (microscopic agglutination test), a standard serological test used to check for Leptospira infection whether it occurred recently or years ago.  The authors mentioned that this was entirely consistent with old studies failing to detect agglutinating antibodies in the sera of some maintenance host animals excreting Leptospira. However, another possibility is that the "chronic human carriers" may have actually acquired asymptomatic infections very recently.  They could have been enrolled in the study before the anti-Leptospira IgM and agglutinating antibodies had enough time the accumulate to the cut-off values selected for the IgM ELISA and MAT, respectively.  Although the authors discounted the possibility of newly acquired asymptomatic infections accounting for the seronegativity of the shedders, they recommended a longitudinal study to clarify the issue.

The authors posed several questions raised by their study:
  • Does persistent Leptospira infection of human kidneys have any subtle effect on their function? If so, is antibiotic treatment warranted?
  • Are some strains of Leptospira more likely than others to persistently infect the kidneys of humans?  .
  • Can persistent human shedders be a source of transmission of Leptospira to other humans (and animals)?
Future studies will need to include urine cultures to demonstrate that Leptospira shed by human carriers are alive.

ResearchBlogging.orgIn conclusion, this is an important study that challenges the simplistic notion that humans are incidental hosts of Leptospira.  The reality appears to be more complicated.

Featured paper

Ganoza, C.A., Matthias, M.A., Saito, M., Cespedes, M., Gotuzzo, E., & Vinetz, J.M. (2010). Asymptomatic renal colonization of humans in the Peruvian Amazon by Leptospira. PLoS Neglected Tropical Diseases, 4 (2) DOI: 10.1371/journal.pntd.0000612

Related paper

Ganoza, C.A., Matthias, M.A., Collins-Richards, D., Brouwer, K.C., Cunningham, C.B., Segura, E.R., Gilman, R.H., Gotuzzo, E., & Vinetz, J.M. (2006). Determining risk for severe leptospirosis by molecular analysis of environmental surface waters for pathogenic Leptospira. PLoS Medicine, 3 (8) DOI: 10.1371/journal.pmed.0030308